Orthopedic Medical Billing Services

Billing for every part of an
orthopedic case

One knee surgery can produce several claims. The surgeon's work. The surgery center. The brace the patient goes home in. The therapy that follows. Each one is billed differently, and each one can be lost on its own. Our orthopedic medical billing services cover all of them.

96%avg. net collection rate across TruCare clients
Book a free demo

What our clients see

96%
average net collection rate across TruCare clients
>95%
clean claim rate, accepted on first submission
−37%
fewer claim rejections
−38%
days in A/R
Figures reflect TruCare client results across specialties, trailing twelve months.

Why orthopedic practices choose TruCare

4.8
Based on 180+ client reviews
Verified client reviews
Jun 03, 2026
Both claims leave together

Our surgery center claims used to trail the surgeon's claims by a week. Now they go out the same day, and I am not matching them up by hand.

Greg Halloran, surgery center director
3 weeks ago
The global period stopped costing us

We were billing visits within the ninety-day window and getting them denied, then writing them off. TruCare showed us which ones were actually billable and how to code the rest.

Dale Fontaine, practice administrator
Apr 21, 2026
Braces finally get paid

Half of our DME claims were failing due to paperwork we did not know we needed. The orders and delivery records are handled now, and the denials have stopped.

N. Patterson, DME coordinator
Mar 08, 2026
Authorizations before the OR date

We are in a state where Medicare now reviews some spine cases first. They file it, track it, and the tracking number is on the claim. Nothing gets scheduled on a maybe.

Dr. Marissa Veloso, orthopedic surgeon
Feb 12, 2026
I can see all four revenue lines

Surgery, therapy, imaging, and DME on one screen, by provider. I used to need three reports and a spreadsheet to get there.

Dr. Simon Achebe, managing partner

What we do, from enrollment to payment

View all services
We get your providers enrolled

TruCred files Medicare, Medicaid, and commercial enrollments and keeps your records current. That includes your surgery center and your supplier enrollment if you dispense braces. Revalidation dates are tracked so nobody drops off.

Medicare enrollmentASC enrollmentDMEPOS enrollment
TruIntake
TruCred
TruRev
TruIntel
TruCare OS

One surgery is billed in four different ways

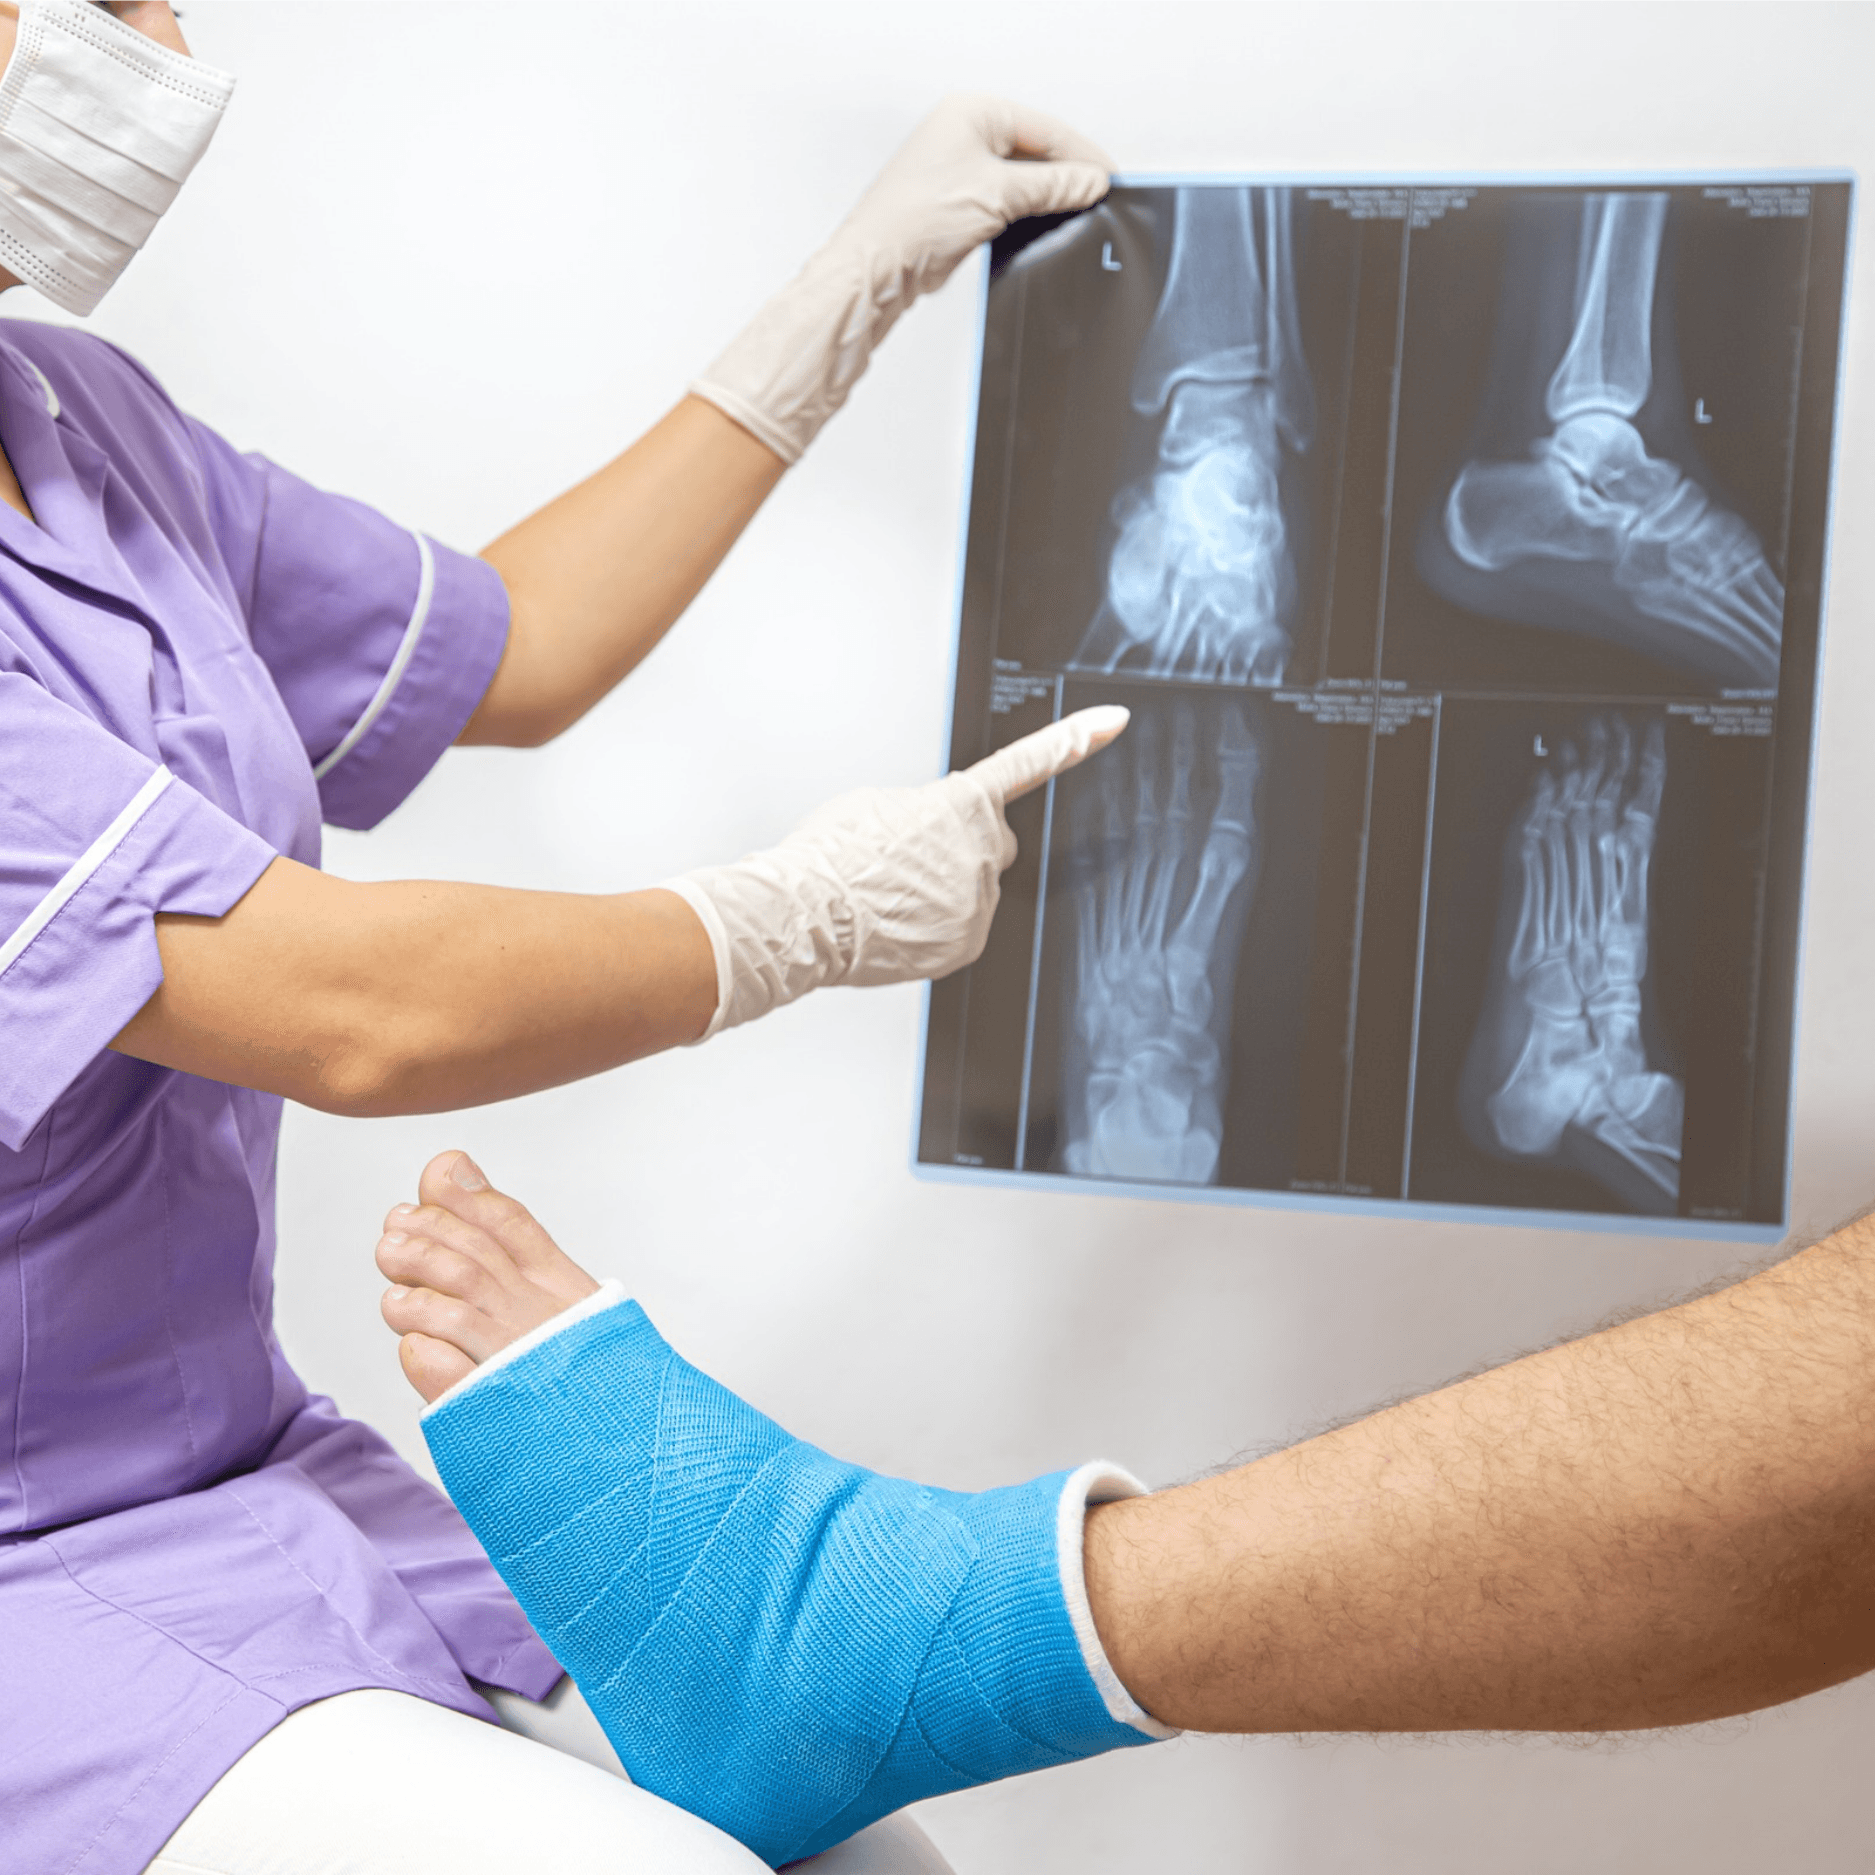
A patient has a knee scoped. The surgeon bills for the operation. If the practice owns the center, the center bills too, on a different form. The patient leaves in a brace, which is its own claim with its own paperwork. Then therapy starts, and that is another stream.

On top of that, the payment for the surgery already includes the follow-up visits. Bill one of those visits the wrong way, and it is denied. Fail to bill the ones that are allowed, and you are working for free.

This is why orthopedics is hard to bill well. The money is not in one place. It is spread across the surgeon, the center, the brace, the X-ray, and the therapy gym, and each piece follows its own rules.

Most billing companies cover the surgeon and leave the rest. That is usually where the missing revenue is.

Six ways an orthopedic claim loses money
The facility claim was never sent
If you own the surgery center, every case is two claims. The professional side gets watched because the surgeons ask about it. The facility side is larger and quieter.
The visit fell inside the global period
After surgery, follow-up care is already paid for. Some visits within that window can still be billed with the right modifier. Billing them without it fails, and not billing them at all means giving up money you earned.
The brace had no paperwork behind it
DME claims need a written order and proof that the patient received the item. Dispense first and document later, and the claim is denied on a technicality.
Two procedures were billed as one, or as three
Multiple procedures in one session follow strict rules about what to reduce, what to bundle, and what needs a separate-site modifier. This is the most common orthopedic coding error we see.
The authorization was missing
Spine procedures, injections, and imaging often need approval first. In six states, Medicare now reviews some of these before the claim is even considered.
The small claims stopped being tracked
Casting supplies, X-rays, injections, therapy visits. None of them is large. Together, they are a meaningful share of what an orthopedic practice earns.

Rated on the platforms that matter

Ratings shown are collected from verified client reviews.
Our service offerings

We bill every orthopedic subspecialty

Knee and sports medicine
Knee and shoulder arthroscopy, ligament reconstruction, and cartilage work. Several procedures often happen through the same scope, and the rules about what is bundled and what stands alone determine most of the payment.
Joint replacement
Hip and knee replacement, including cases that have moved out of the hospital. Medicare has paid surgery centers for total knee since 2020 and total hip since 2021. High-value claims with a ninety-day global period behind them, so the follow-up care has to be handled correctly too.
Spine
Fusions, decompressions, and injections. Among the most authorization-heavy work in orthopedics, in six states, Medicare now reviews cervical fusion and epidural steroid injections before they happen. Levels, approaches, and second surgeons all change the claim.
Hand and upper extremity
Carpal tunnel, trigger finger, fracture fixation, and tendon repair. Many small procedures, often several in one visit, each needing the right finger and the right side reported, or the claim is denied.
Foot and ankle
Bunion correction, fusions, tendon work, and fracture care. Several procedures on the same foot in one session follow strict bundling rules, and total ankle replacement joined the surgery center list in 2024.
Shoulder and elbow
Rotator cuff repair, instability procedures, and replacement. Arthroscopic shoulder cases are among the most heavily bundled in the code set, so the coding has to follow the operative note closely. Shoulder replacement also became payable in surgery centers in 2024.
Orthopedic trauma
Fracture care is billed either as a complete episode or as a visit with supplies, plus casting, splinting, and hospital consults. The choice between those two billing paths changes what you are paid.
Pediatric orthopedics
Fracture care, deformity correction, and the repeat visits that come with growing patients. Often a heavier Medicaid mix, which means different authorization rules and different documentation requirements.

How we fit into your practice

Coders who read operative notes
Your claims are handled by certified billers and coders who work on orthopedic cases. They code from the note, not from the scheduled procedure, because those are often different.
One team across all your revenue
Surgery, the center, therapy, imaging, and DME are handled together rather than split between a biller and whoever has time. Nothing falls between two desks.
No new software for your staff
We work on top of the system your practice already uses, including Epic, Athenahealth, eClinicalWorks, AdvancedMD, and Elation. No migration and no second login.

The denials orthopedic practices see most

Orthopedic denials are rarely arguments about the surgery. They are arguments about a modifier, a date, or a piece of paperwork that was supposed to exist before the patient went home.

Most of them are preventable at submission, so that is where we put the work.

Want to know what your denials are costing you?
Send us 90 days, and we will show you the pattern.
Request a billing audit
Here is what we catch first:
Missing or wrong modifier on a multi-procedure case

When several procedures happen in one session, the modifiers decide whether each one is paid, reduced, or dropped. This is the single biggest source of lost orthopedic revenue.

A visit billed inside the global period

Follow-up care is included in the surgical payment. Billing a routine post-op visit on its own gets denied every time. Billing an unrelated problem without the right modifier gets denied too.

No authorization on file

Spine procedures, injections, and imaging commonly need approval first, and in six states, Medicare now reviews some of them in advance. Without it, the claim does not get a fair hearing.

DME paperwork gaps

A brace billed without a written order or proof of delivery will be denied and will fail an audit later, even if it is paid now.

Assistant surgeon not supported

When a second surgeon assists, the claim needs the right modifier, and the note has to show why the help was necessary. Payers check this closely.

Left or right not specified

Orthopedics is a side-specific specialty. A claim without laterality, or with the wrong side, is denied or creates a bigger problem later.

The modifiers that decide what you get paid

Our orthopedic billing & medical coding services run on a small set of modifiers. Orthopedic codes are not the hard part. The modifiers are. Two surgeries with the same procedure code can pay very differently depending on which letters and numbers ride along with them.

Our coders work orthopedic cases every day. They know what each modifier does, when a payer will ask for the note, and which combinations draw attention.

Book a free consultation
The ones that matter most:
Modifiers 24587879
Working inside the global period

An unrelated visit, a planned second stage, a return to the operating room, and a completely separate procedure. Four different situations, four different modifiers, all within the window where care is otherwise included.

Keep the EHR your office runs on

Nothing about your clinic or OR day changes. TruCare connects to Epic, athenahealth, eClinicalWorks, AdvancedMD, Elation, and the other systems practices use, so visits, operative notes, therapy records, and dispensing logs come across on their own. No migration weekend. No second login for your schedulers or therapists.

The difference shows up in what does not slip. A facility claim that never went out. A post-op visit coded without its modifier. A brace with no delivery record. An appeal with a deadline this week. Those land on a worklist instead of in next month's denial report.

See a demo with your EHR

Deep integrations with all EHRs

TruCare connects seamlessly with your existing workflows — no switching required.

Epic
MEDITECH
Cerner
athenahealth
EXPERITY
eClinicalWorks
AdvancedMD
Kareo
WebPT
Axxess
inSync
Epic
MEDITECH
Cerner
athenahealth
EXPERITY
eClinicalWorks
AdvancedMD
Kareo
WebPT
Axxess
inSync
Epic
MEDITECH
Cerner
athenahealth
EXPERITY
eClinicalWorks
AdvancedMD
Kareo
WebPT
Axxess
inSync
Clinicient
Altera Digital Health
Cerbo
hellonote
Jane
Nexus Clinical
drchrono
HealthCare Synergy
Office Ally
Elation
Lightning Step
Clinicient
Altera Digital Health
Cerbo
hellonote
Jane
Nexus Clinical
drchrono
HealthCare Synergy
Office Ally
Elation
Lightning Step
Clinicient
Altera Digital Health
Cerbo
hellonote
Jane
Nexus Clinical
drchrono
HealthCare Synergy
Office Ally
Elation
Lightning Step

What changed for orthopedics in 2026

Medicare now reviews some procedures first
The WISeR model started on January 1, 2026, in Arizona, New Jersey, Ohio, Oklahoma, Texas, and Washington. It applies to dates of service from January 15 onward, and the list includes epidural steroid injections, cervical fusion, knee arthroscopy for osteoarthritis, and vertebral augmentation.
Those claims need a tracking number
When a procedure on that list is approved, the approval comes with a unique tracking number that has to appear on the claim. Submit without it, and the claim is reviewed before anything is paid.
Hospitals moved into mandatory bundles
CMS launched the TEAM model on January 1, 2026 for selected hospitals, running through 2030. Three of its five episode types are orthopedic: joint replacement, hip and femur fracture surgery, and spinal fusion.
That changes how hospitals talk to surgeons
TEAM applies to hospitals, not to your practice. But a hospital accountable for 30 days after surgery cares a great deal about who operates, where cases go afterward, and what the readmission rate looks like.
Surgical codes lose work value
The 2026 fee schedule applies an efficiency adjustment of 2.5 percent to the work value of codes that are not billed by time. Surgical codes sit in that group.
There are now two conversion factors
Medicare pays at one rate for practices in qualifying advanced payment models and another for everyone else. Which one applies to you is worth confirming.

How we keep rule changes from costing you

Someone has to read the annual rule, the code set, and each payer bulletin. That is part of what you are paying us for.

When an authorization requirement appears, or a value moves, it goes into our claim checks before your first claim of the year goes out.

We also read the remittance rather than just posting it. If a payer pays below your contracted rate, we raise it instead of absorbing it.

In-house vs. outsourced

Can one billercover a surgical practice?

An in-house biller knows your surgeons and your patients. A surgical practice also asks that person to cover operative coding, facility claims, global periods, therapy, imaging, and DME. Whether one desk can handle all of that is the honest question.

The questionOne in-house billerTruCare
Operative codingCoded from the schedule when the note is lateCoded from the note, every case
ModifiersThe most common source of lost revenue, left to one personChecked on every multi-procedure case before submission
Facility claimsA second job nobody formally ownsBilled alongside the professional claim
Global periodsPost-op visits denied, then written offTracked by case, with the right modifier when one applies
DME and therapyBilled when there is timeHandled as part of the same workflow
AuthorizationsChased the week of surgeryFiled early and tracked to the decision
Code and policy changesNoticed when denials appearBuilt into claim checks when they take effect
Cost shapeSalary, benefits, training, softwareA percentage of collections, so it moves with volume
Absence and turnoverOne departure stalls months of billingCoverage is our problem, not your office manager's
What the owner seesA report built on requestRevenue by surgeon and by service line, live
Want to see where your practice stands? Send us 90 days of denials and aging A/R.
Hover a state to see coverage
Where we serve

Orthopedic billing in every state

We work with solo surgeons, multi-site orthopedic groups, physician-owned surgery centers, sports medicine practices, and joint replacement programs. Rules differ by state, by Medicare contractor, and now by whether your state is in the prior authorization model, so we handle them one at a time.

Prior authorization
ASC and professional billing
DME and orthotics
Therapy and imaging
Multi-state enrollment
A named account contact
Who we bill every day
Medicare Part B
Surgical coverage rules, contractor policies, and the new authorization requirements
Medicare Advantage
Authorization rules that differ plan by plan
Medicaid and managed Medicaid
State programs and MCO plans
BCBS and Anthem
Surgical and DME policies that vary by plan
Centene family
Molina, WellCare, Amerigroup
Other
VA Community Care, self-pay, and cash-pay sports medicine
We bill whatever plans your practice is contracted with. If you are not contracted yet, TruCred handles the enrollment.

Orthopedic billing saver guide

A practice collecting $1.4 million saves up to $38,200 a year by outsourcing to TruCare
In-house billingWith TruCareAnnual saving
Dedicated billing staff$73,060$0$73,060
Billing software and clearinghouseVariesIncluded—
Training, turnover, and coverageVariesIncluded—
TruCare fee (from 2.49% of collections)—$34,860—
Total annual cost$73,060$34,860$38,200
Example: a practice collecting $1.4 million a year with one full-time biller, at TruCare's starting rate of 2.49%. Biller cost uses the BLS May 2025 median wage for medical records specialists ($51,140), with benefits at 30% of total compensation. Software and training costs vary by practice and are not counted. We do not replace your front desk; we take the claims work off it. Larger groups are quoted on volume rather than at the starting rate, so a bigger practice should not scale this example up.
Want this run on your own numbers?
Talk to an orthopedic billing expert

What changes after the first quarter

““The surgeons were never the problem. Their claims went out and got paid. What nobody owned was everything around the surgery: the center claims, the braces, the therapy visits. Once all of it sat with one team, we found money we had been giving away for years.””

Dr. Simon Achebe
managing partner, Granite Ridge Orthopedics

We use cookies to understand how visitors use our site and to improve your experience. You can accept or decline analytics cookies. See our Privacy Policy for details.