TruCare
Anesthesia Billing Services

Anesthesia billing for
every case you cover

An anesthesia claim is built from three things. The base units for the procedure. The minutes you were with the patient. And the modifier that says who was in the room. Get one wrong, and the whole claim is wrong. Our anesthesia billing services check all three before the claim goes out.
96%avg. net collection rate across TruCare clients
Masked healthcare worker in blue gloves draws vaccine from a vial labeled COVID-19 into a syringe.
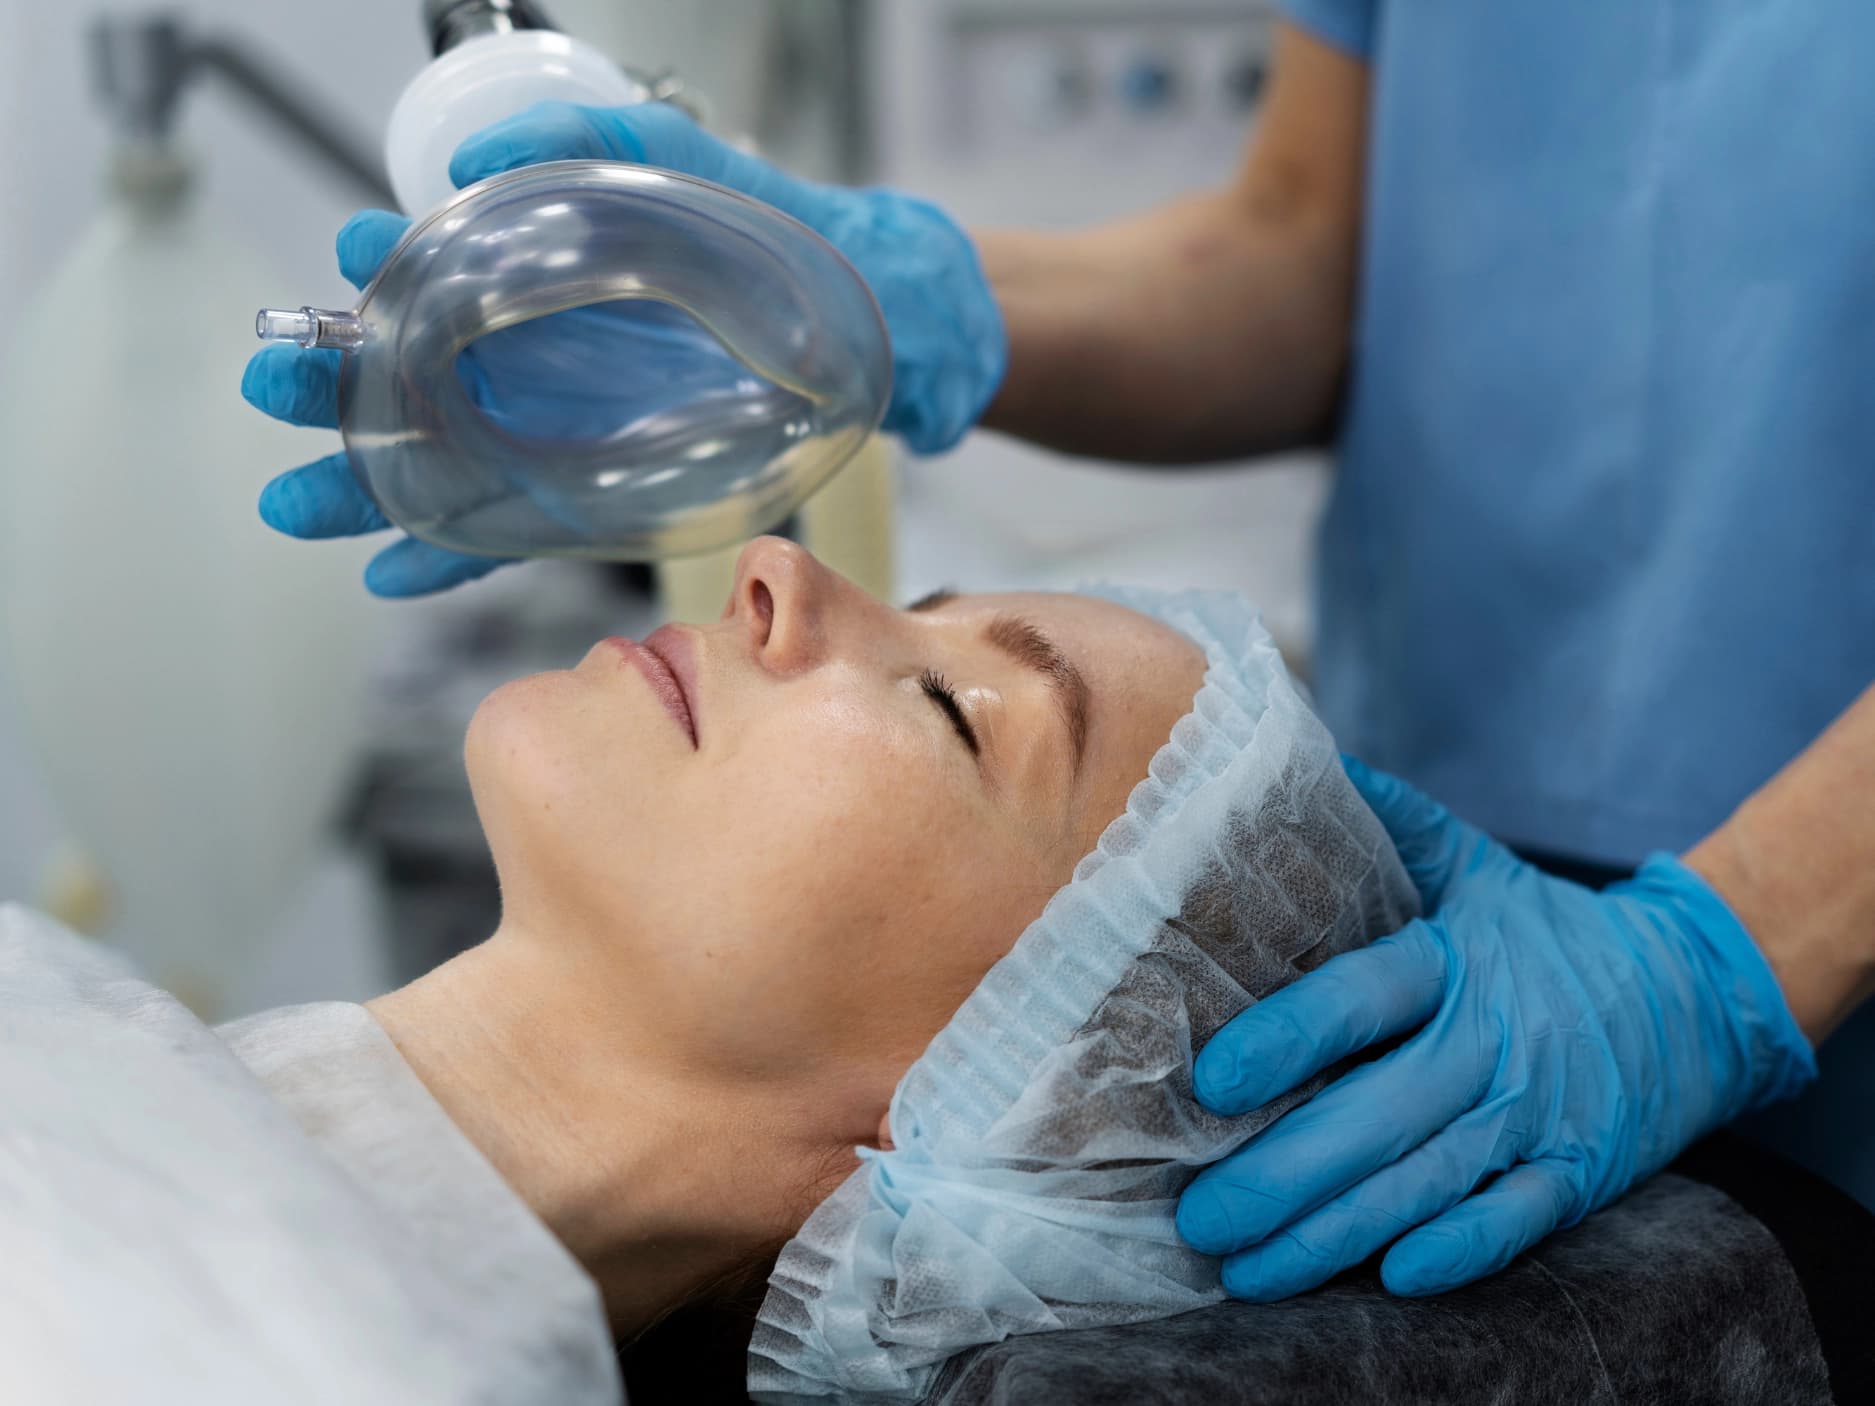
Gloved hands hold an anesthesia mask over the face of a sedated patient wearing a surgical cap.
Three colleagues sit together looking at a laptop screen during a meeting in a modern office.
See your numbers

Results across TruCare clients

96%
average net collection rate across TruCare clients
>95%
clean claim rate, accepted on first submission
−37%
fewer claim rejections
−38%
days in A/R
Figures reflect TruCare client results across specialties, trailing twelve months.

Why groups choose our anesthesia medical billing services

Rated 4.8 / 5
Based on 180+ client reviews
Verified client reviews
Oct 13, 2026
The modifiers finally match the schedule
We run a care team model, and half our denials came from modifiers that did not match who was actually in the room. They rebuilt how we capture that. The denials stopped.
Colleen Hargrove, group administrator
last week
Times that hold up
We lost claims over start and stop times that overlapped between rooms. Now every case is checked against the schedule before it is billed.
Tomas Wieland, billing manager
Aug 25, 2026
Pain claims got their tracking numbers
Our pain clinic is in a state where Medicare now reviews some procedures first. They file the request and put the tracking number on the claim. Nothing goes out without it.
Yara Haddock, pain practice manager
Jul 14, 2026
New hires bill in weeks
We rotate CRNAs and locums across five facilities. Enrollment used to hold them up for months. Now it runs alongside onboarding.
Anil Deshmukh, chief CRNA
Jun 02, 2026
One report across every site
Units per case, collections by facility, denials by reason. I used to build that in a spreadsheet at the end of each month. It is just there now.
Dr. Winston Hale, managing partner

What we do between the case and the payment

View all services
We get every clinician enrolled
TruCred files enrollments for anesthesiologists, CRNAs, and anesthesiologist assistants, and keeps them current across every facility you cover. New hires and locums are enrolled in parallel with onboarding, and revalidation dates are tracked.
Provider enrollmentMulti-facilityRevalidation
TruIntake
TruCred
TruRev
TruIntel
TruCare OS

Anesthesia is paid by formula, not by fee.

Most specialties have a fee for each service. Anesthesia does not. Every claim is a calculation. Base units for the procedure, plus time units for the minutes, plus any modifying units, all multiplied by a conversion factor.
That makes every input matter. A wrong code changes the base units. A missing stop time changes the minutes. A wrong modifier changes who gets paid, and how much.
Then the care team adds a second layer. When an anesthesiologist directs a CRNA, Medicare splits the payment between them. How many cases the physician directed at once, and what they did in each one, decides the modifier on both claims.
This is why general billing companies struggle here. The claim looks short. The decisions behind it were made in the operating room, and they only count if they were written down there.
Six ways an anesthesia claim loses money
The care model was billed the wrong way
A physician who performed the case, directed a CRNA, or supervised several rooms is billed under a different modifier in each situation. Choose wrong and the claim is reduced, or denied outright.
The minutes did not hold up
Time is the largest part of most payments. Missing stop times, overlapping times across rooms, and rounded numbers all weaken the claim and draw review.
The concurrency was not tracked
Payment drops when a physician directs more cases at once than the rules allow. Nobody notices until the remittance shows the difference.
The anesthesia code did not match the surgery
Each surgical procedure maps to a specific anesthesia code. Pick the wrong one and the base units are wrong before the clock even starts.
The pain procedure went out without approval
Some injections and implants need approval first. In six states, Medicare reviews certain ones before it will consider the claim.
A case at a smaller site never reached billing
Endoscopy suites and dental offices do not run through the hospital’s systems. Cases there are easy to lose between the schedule and the claim.

Rated on the platforms that matter

Google rating 4.8 out of 5Trustpilot rating 4.8 out of 5BBB accredited business, A+ rating
Ratings shown are collected from verified client reviews.
Our service offerings

Every kind of case your clinicians cover

Hospital operating rooms
The core of most groups. Several rooms running at once, which means the concurrency rules and the medical direction record have to hold up for every case.
Surgery centers
Shorter cases, faster turnover, and facility contracts that differ from the hospital’s. Time and unit accuracy matter more here because the cases are quick.
Obstetric anesthesia
Labor epidurals billed by time, and cases that start as one service and become another. A labor epidural that ends in a cesarean is reported in a specific way.
Pediatric anesthesia
Younger patients, different age rules, and a heavier Medicaid mix. Some payers pay an extra unit for patients at the youngest and oldest ends of the age range.
Office-based GI endoscopy
Anesthesia for colonoscopy and upper endoscopy outside the hospital. Coverage for routine screening cases varies by plan, and a screening that turns diagnostic changes how the anesthesia is coded.
Dental anesthesia
General anesthesia and sedation in dental offices, often for children and for patients with special needs. Coverage depends on the plan and on a documented reason.
Interventional pain management
Epidural steroid injections, nerve blocks, and implants. Some codes include the imaging guidance and some do not, and several procedures now carry approval requirements.
Monitored anesthesia care
Sedation with the anesthesia provider monitoring the patient throughout. It has its own set of modifiers, and which one applies depends on the case and the patient’s history.

How we fit into your group

Coders who read the anesthesia record
Your claims are handled by certified billers and coders who work anesthesia accounts. They know the care-team modifiers and what the record has to show to support each one.
Enrollment that follows your rotation
Clinicians move between facilities, and locums come and go. TruCred keeps the enrollments current so a new name on the schedule does not mean a delayed claim.
Keep the record system you already use
We work from the system your group already charts in, including Epic, MEDITECH, and Cerner. No migration and no second login for your clinicians.

The denials anesthesia groups see most

Anesthesia denials are rarely about whether the care was needed. They are about whether the record can prove the formula. Who was there, for how long, and doing what.
Most can be caught before the claim goes out, which is where we put the effort.
Not sure what your denials are costing you?
Send us 90 days and we will show you the pattern.
Request a billing audit
Here is what we catch first:
Masked surgeon in a surgical cap holds up a syringe with a needle, looking intently at the camera.
Wrong modifier for the care model
The physician side and the CRNA side each need a modifier that matches what actually happened. A mismatch between the two claims is a routine denial.
Medical direction not documented
Medicare requires specific steps from a directing physician, and the record has to show them. Without it, the claim is paid as supervision rather than direction, which is much less.
Anesthesia time not supported
Start and stop times have to be in the record and have to make sense against the surgical case. Overlaps across rooms are a common reason claims are pulled for review.
Wrong anesthesia code for the procedure
The anesthesia code has to match the surgical code. A mismatch changes the base units and often triggers an automatic denial.
A converted screening coded as a screening
When a screening colonoscopy becomes diagnostic, the anesthesia has to be coded differently and carry a modifier. Missing it changes what the patient owes.
Pain procedure with no approval or tracking number
In the six states with prior authorization, the approval comes with a tracking number that has to appear on the claim. Without it, the claim is held for review before payment.

The formula and modifiers behind every claim

Our anesthesia billing and coding services run on one formula and a short list of modifiers. Every claim is built from the same parts, and each part comes from a different place. The code, the clock, the care team, and the patient.
Walk through your coding with us
The ones that matter most:
The payment formula
Three kinds of units
Base units, time units, and modifying units are added together and multiplied by the anesthesia conversion factor. Each kind comes from a different part of the record.

We pull from the anesthesia record you already keep

Nothing about your day in the OR changes. TruCare connects to the systems your group already charts in, including Epic, MEDITECH, and Cerner, so times, staffing, and procedure details reach billing on their own. No migration weekend. No second login for your clinicians.
What changes is what gets noticed. A case with no stop time. A modifier that does not match who was staffed. A pain procedure with no approval on file. A converted screening coded as a screening. Those appear on a worklist while they can still be fixed.
Check for your system
Sedated man wearing an oxygen mask lies back as a medical worker in scrubs attends to him, with a white logo in the corner.

Deep integrations with all EHRs

TruCare connects seamlessly with your existing workflows — no switching required.

Epic
MEDITECH
Cerner
athenahealth
EXPERITY
eClinicalWorks
AdvancedMD
Kareo
WebPT
Axxess
inSync
Epic
MEDITECH
Cerner
athenahealth
EXPERITY
eClinicalWorks
AdvancedMD
Kareo
WebPT
Axxess
inSync
Epic
MEDITECH
Cerner
athenahealth
EXPERITY
eClinicalWorks
AdvancedMD
Kareo
WebPT
Axxess
inSync
Clinicient
Altera Digital Health
Cerbo
hellonote
Jane
Nexus Clinical
drchrono
HealthCare Synergy
Office Ally
Elation
Lightning Step
Clinicient
Altera Digital Health
Cerbo
hellonote
Jane
Nexus Clinical
drchrono
HealthCare Synergy
Office Ally
Elation
Lightning Step
Clinicient
Altera Digital Health
Cerbo
hellonote
Jane
Nexus Clinical
drchrono
HealthCare Synergy
Office Ally
Elation
Lightning Step

What changed for anesthesia in 2026

Anesthesia now has two conversion factors
For 2026, Medicare pays anesthesia at $20.5998 per unit for clinicians in qualifying advanced payment models and $20.4976 for everyone else. In 2025 there was a single rate of $20.3178.
The increases are modest
The two rates are up 1.39 percent and 0.88 percent from the 2025 rate. Which one applies to your clinicians is worth confirming.
Part of the increase is for one year only
The 2026 rates include a one-time payment boost from Congress. It does not carry into 2027, so the increase should not be built into long-term plans.
The headline rate is not the whole story
CMS also adjusted the practice expense and malpractice part of the anesthesia fee schedule when it set the final rates. Check what your own payments look like, not just the published factor.
Some pain procedures need approval in six states
CMS launched the WISeR model on January 1, 2026 in Arizona, New Jersey, Ohio, Oklahoma, Texas, and Washington. For dates of service from January 15 onward, the list includes epidural steroid injections, vertebral augmentation, and certain nerve stimulator implants.
Those claims need a tracking number
When a procedure on that list is approved, the approval comes with a unique tracking number that has to appear on the claim. Submit without it, and the claim is reviewed before anything is paid.

Who is watching the rules for you

Someone has to read the fee schedule, the conversion factors, and each payer’s bulletins. In a busy group, that rarely gets done.

We read them, and we turn each change into a check that runs before your claims go out.
We also read every remittance against your contract. If a payment comes in below what you should have received, we raise it rather than absorbing it.
In-house vs. outsourced

Can one biller keep up with a care team?

An in-house biller knows your clinicians and your facilities. An anesthesia group also asks that person to read modifiers off staffing sheets, check times against the schedule, track concurrency, and chase approvals. Outsourcing anesthesia billing services brings people who handle the care-team modifiers across many groups. Whether one desk can hold all of it is the honest question.
The questionOne in-house billerTruCare
Care-team modifiersApplied from memory, case by caseMatched to who was staffed, every claim
Anesthesia timeTaken as writtenChecked against the surgical case and the other rooms
ConcurrencyNoticed when payment dropsTracked against the limits as cases are billed
Anesthesia codePicked from habitChecked against the surgical code
Pain approvalsChased the week of the procedureFiled early, with the tracking number on the claim
Smaller sitesCases fall between systemsReconciled against the schedule
New cliniciansEnrollment delays billing for monthsEnrolled in parallel with onboarding
Cost shapeSalary, benefits, training, softwareA percentage of collections, so it moves with volume
Absence and turnoverOne departure stalls billing for weeksStaffing the desk is on us
What the owner seesA report built at month endUnits per case and collections by site, live
Compare against your numbersWant to see where your group stands? Send us 90 days of denials and aging A/R.
Hover a state to see coverage
Where we serve

Anesthesia billing in every state

We work with anesthesia groups, CRNA-led practices, interventional pain practices, surgery-center groups, and clinicians who provide anesthesia in offices and endoscopy suites. Coverage rules differ by state and by plan, and some now differ by whether your state is in the Medicare prior authorization model, so we handle them one at a time.
Care-team billing
Pain authorizations
Office-based anesthesia
Multi-facility enrollment
Denial and appeal management
A named account contact
Who we bill every day
Medicare Part B
Medical direction rules, concurrency limits, and the two 2026 conversion factors
Medicare Advantage
Authorization and payment rules that differ plan by plan
Medicaid and managed Medicaid
State programs and MCO plans, including pediatric cases
BCBS and Anthem
Contracted rates and plan-by-plan payment rules
Centene family
Molina, WellCare, Amerigroup
Other
VA Community Care and self-pay
We bill whatever plans your group is contracted with. If you are not contracted yet, TruCred handles the enrollment.

Anesthesia billing saver guide

A group collecting $850,000 saves up to $51,895 a year by outsourcing to TruCare
In-house billingWith TruCareAnnual saving
Dedicated billing staff$73,060$0$73,060
Billing software and clearinghouseVariesIncluded—
Training, turnover, and coverageVariesIncluded—
TruCare fee (from 2.49% of collections)—$21,165—
Total annual cost$73,060$21,165$51,895
Example: a group collecting $850,000 a year with one full-time biller, at TruCare’s starting rate of 2.49%. Biller cost uses the BLS May 2025 median wage for medical records specialists ($51,140), with benefits at 30% of total compensation. Software and training costs vary by group and are not counted. We do not replace your front desk, we take the claims work off it. Larger groups are quoted on volume rather than at the starting rate, so a bigger group should not scale this example up.
Want this run on your own numbers?
Talk to an anesthesia billing expert

Six months in

“We always assumed anesthesia billing was just minutes and a conversion factor. Then someone read our modifiers against who was actually staffed, and we found two years of claims that had been paid as supervision instead of direction. The fix was not complicated. Nobody had been checking.”
Dr. Beatrice Okoye
Managing partner, regional anesthesia group

We use cookies to understand how visitors use our site and to improve your experience. You can accept or decline analytics cookies. See our Privacy Policy for details.