TruCare
Cardiology Billing Services

We bill the tests
your heart patients need

Most specialties send one claim per visit. Cardiology sends several, from one order. The reading, the equipment, the test itself, each billed on its own terms, each needing its own proof. Miss one piece and the claim for it simply does not go out. Our cardiology billing services catch every piece before that happens.
96%avg. net collection rate across TruCare clients
Anatomical heart model next to a stethoscope laid out on a light blue background.
Doctor checks a patient's blood pressure using an arm cuff and monitor.
Businessman in a suit reviews notes beside his laptop while working at a cafe table.
See your numbers

How TruCare clients perform

96%
average net collection rate across TruCare clients
>95%
clean claim rate, accepted on first submission
−37%
fewer claim rejections
−38%
days in A/R
Figures reflect TruCare client results across specialties, trailing twelve months.

Why cardiology groups choose our cardiology medical billing services

Rated 4.8 / 5
Based on 180+ client reviews
Verified client reviews
Oct 06, 2026
We were billing only the reading
We own our echo and stress equipment and employ the sonographers, but only the interpretation was going out. They found it in the first month. That alone changed our revenue.
Gwen Ashby, practice administrator
2 weeks ago
Approvals before the appointment
Our patients were showing up for a cardiac CT and we were learning afterwards that the plan wanted approval first. That does not happen anymore.
Fiona Lindgren, imaging manager
Aug 19, 2026
Repeat studies stopped denying
We kept losing claims on follow-up tests ordered close together. They showed us what the note has to say and which modifier applies.
Dr. Ahmed Rahimi, cardiologist
Jul 08, 2026
The cath lab claims go out together
Facility and physician claims used to leave on different days. Now they leave together, and I am not matching them by hand.
Joanne Pruitt, cath lab manager
Jun 11, 2026
One report for every service line
Visits, imaging, procedures, and rehab by physician on one screen. I used to need four reports and a spreadsheet to see that.
Dr. Camille Dubois, managing partner

What we do, from the first order to the last payment

View all services
We get your clinicians and your sites enrolled
TruCred files Medicare, Medicaid, and commercial enrollments for physicians, advanced practice providers, and your imaging or cath lab sites. Revalidation dates are tracked so nobody drops off a panel.
Provider enrollmentSite enrollmentRevalidation
TruIntake
TruCred
TruRev
TruIntel
TruCare OS

A cardiology visit is never just a visit.

A patient comes in with chest pain. The cardiologist sees them, and an ECG is done in the room. An echo is scheduled for the afternoon. A stress test follows next week. If something shows up, a cath is booked.
That is five or six services from one problem, and each one is billed separately. Each needs its own order. Each needs a diagnosis that supports it. If you own the equipment, each has a technical side and a reading side.
Every one of those pieces is a place a claim can fail. The test is paid only when the diagnosis on the claim supports it under that plan’s rules. Many plans want approval first. Repeat tests get extra attention, and so do same-day visits.
General billing companies handle the visit well and lose the rest. In cardiology, the rest is most of the revenue.
Six places cardiology revenue slips away
Only the reading was billed
If you own the equipment and employ the technologist, you are owed for the study as well as the interpretation. Practices that bill only the reading give away the larger half.
The test had no diagnosis behind it
A test is paid when the diagnosis on the claim supports it. An order with a vague diagnosis is denied, even when the test was clearly needed.
The visit was dropped
An office visit on the same day as a procedure needs a modifier and a note that stands on its own. Without both, only the procedure is paid.
The facility claim never went out
If you own the cath lab or the surgery center, every case has two claims. The physician side gets watched. The facility side is easy to lose.
The approval was missing
Advanced imaging and procedures often need approval first. Without it, the claim is denied after the test has already been done.
A repeat test was billed without support
Ordering the same test again within a short time needs a reason in the record and the right modifier. Without them, it is denied as a duplicate.

Rated on the platforms that matter

Google rating 4.8 out of 5Trustpilot rating 4.8 out of 5BBB accredited business, A+ rating
Ratings shown are collected from verified client reviews.
Our service offerings

From the clinic to the cath lab

General cardiology
Office visits, ECGs, consults, and the long-term care of patients with heart disease. The volume work in every practice, coded to the documentation rather than to habit.
Interventional cardiology
Diagnostic cath and coronary procedures, several often in one session. PCI codes were revised for 2026, so the coding has to follow the current set.
Electrophysiology
Rhythm studies, ablation, and in-person pacemaker and defibrillator checks and implants. High-value procedures with their own bundling rules and documentation.
Cardiac imaging
Echo, nuclear, cardiac CT and MRI, billed as the full study or split between the images and the reading, depending on who owns the equipment.
Vascular and peripheral work
Lower extremity procedures, which were rebuilt in 2026 under 46 new codes. The older codes were deleted, so a charge sheet from last year will not hold.
Heart failure and structural care
Long-term follow-up, medication management, and procedures for valves and structure. Authorization-heavy work with long episodes of care.
Preventive cardiology
Risk assessment, lipid management, and screening, with the line between preventive and diagnostic care deciding what the patient owes.
Cardiac rehabilitation
Supervised exercise and education programs, billed by session with their own limits, supervision rules, and referral requirements.

What it is like to work with us

Coders who read the cath report
Your claims are handled by certified billers and coders who work cardiology accounts. They know what a stress test report has to show, and which procedures bundle when done together.
One team across tests and procedures
Visits, imaging, the cath lab, and rehab handled together rather than split between desks. Nothing falls between two people.
Keep the EHR you already use
We work on top of the system your practice already runs on, including Epic, Cerner, athenahealth, and eClinicalWorks. No migration and no second login for your sonographers or nurses.

The six denials that cost cardiology groups most

Cardiology denials are rarely about whether the test was needed. They are about whether the record proves it. A diagnosis, a report, a modifier, an approval.
Most can be stopped before the claim is built, which is where we put the work.
Not sure what your denials are costing you?
Send us 90 days and we will show you the pattern.
Request a billing audit
Here is what we catch first:
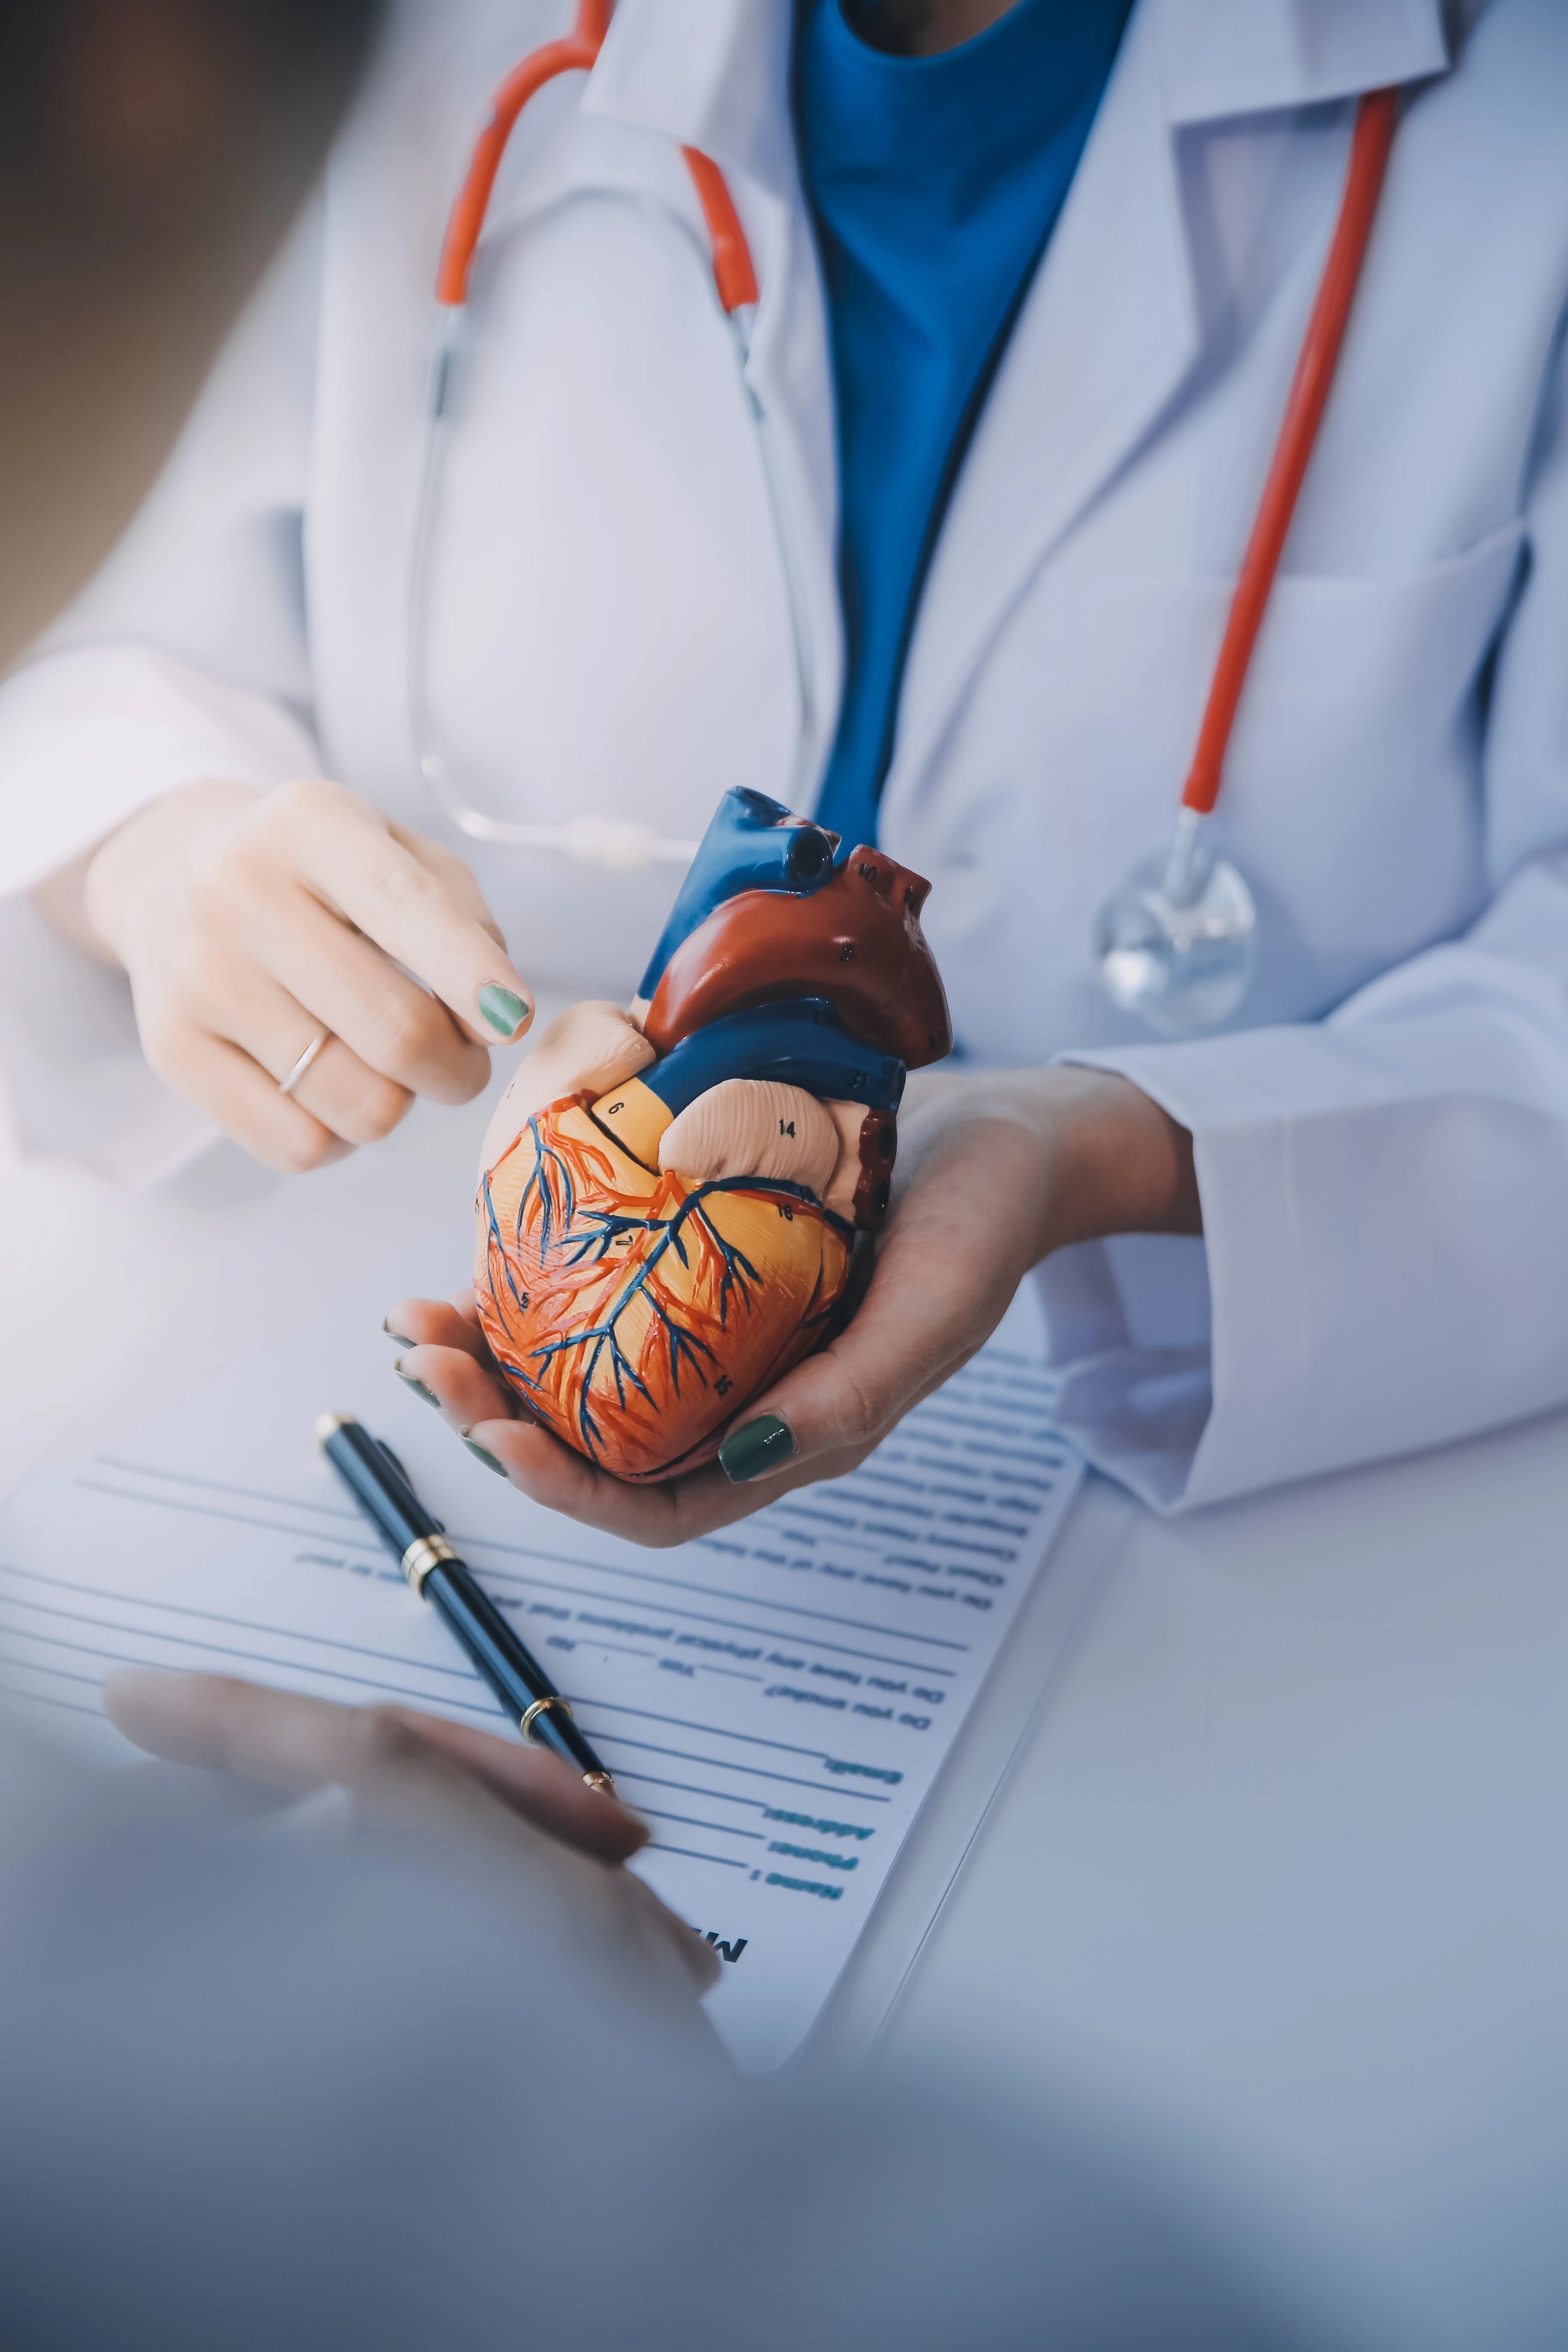
Doctor in a white coat holds an anatomical heart model while pointing to it with a pen over a clipboard.
The diagnosis does not support the test
Each plan lists the conditions it will pay a test for. If the diagnosis on the claim is not on that list, the claim is denied however good the reason.
The interpretation report is missing or unsigned
A test cannot be billed for its reading without a signed report. A missing signature turns a paid study into a denial.
A repeat study without the right modifier
The same test twice in a short time needs a modifier and a reason in the note. Without them, it is treated as a duplicate.
Same-session procedures billed wrongly
Several procedures in one cath session follow strict rules about what bundles and what stands alone. Billing them separately when they bundle gets the claim reduced.
No approval on file
Plans commonly require approval before advanced imaging and procedures. We check the requirement before the date is booked, not after the test.
Cardiac rehab past its limits
Rehab is covered for specific conditions, with a cap on sessions, a referral, and supervision requirements. Treating past the limit, or without the paperwork, means the visits are not paid.

The codes and modifiers cardiology claims depend on

Our cardiology billing and coding services cover a set of codes used thousands of times a year, and the modifiers that decide whether each one holds. Our coders work cardiology charts every day and know where groups lose money.
Walk through your coding with us
The ones that matter most:
930009300593010
ECG
The complete ECG, the tracing alone, and the interpretation alone. Which one applies depends on who recorded the tracing and who read it.

We connect to the systems your cardiologists already use

Nothing about your clinic day changes. TruCare connects to Epic, Cerner, athenahealth, eClinicalWorks, and the other systems practices use, so visits, orders, test reports, and procedure notes reach billing on their own. No migration weekend. No second login for your imaging staff.
What changes is what gets noticed. A test ordered without a supporting diagnosis. A study billed without its technical half. An approval that has not come back. An interpretation still waiting for a signature. Those appear on a worklist while they can still be fixed.
Check for your EHR
Doctor listens to a smiling woman's heart with a stethoscope, with a white logo in the corner.

Deep integrations with all EHRs

TruCare connects seamlessly with your existing workflows — no switching required.

Epic
MEDITECH
Cerner
athenahealth
EXPERITY
eClinicalWorks
AdvancedMD
Kareo
WebPT
Axxess
inSync
Epic
MEDITECH
Cerner
athenahealth
EXPERITY
eClinicalWorks
AdvancedMD
Kareo
WebPT
Axxess
inSync
Epic
MEDITECH
Cerner
athenahealth
EXPERITY
eClinicalWorks
AdvancedMD
Kareo
WebPT
Axxess
inSync
Clinicient
Altera Digital Health
Cerbo
hellonote
Jane
Nexus Clinical
drchrono
HealthCare Synergy
Office Ally
Elation
Lightning Step
Clinicient
Altera Digital Health
Cerbo
hellonote
Jane
Nexus Clinical
drchrono
HealthCare Synergy
Office Ally
Elation
Lightning Step
Clinicient
Altera Digital Health
Cerbo
hellonote
Jane
Nexus Clinical
drchrono
HealthCare Synergy
Office Ally
Elation
Lightning Step

How 2026 changed cardiology payment

Medicare now pays at two rates
There are two conversion factors for the first time. One applies to clinicians in qualifying advanced payment models, and one applies to everyone else. Worth confirming which applies to you.
CMS expects a small net gain for cardiology
CMS estimates the finalized changes raise cardiology payments by about 1 percent. The result depends heavily on your mix of services.
Tests and procedures lost work value
The 2026 fee schedule applies an efficiency adjustment of 2.5 percent to the work value of nearly all codes that are not billed by time. The American College of Cardiology says it hits procedural and diagnostic services hardest.
The cut comes back every three years
CMS will apply the adjustment again every three years. New codes created and valued for 2026 were exempted.
Leg revascularization was rebuilt
Codes 37220 to 37235 were deleted and replaced with 46 new codes. Coronary stenting also gained new codes for complex cases, and a new code covers software-assisted plaque analysis on cardiac CT.
Office visits were spared
Visits are billed by time or decision making, not as procedures, so they sat outside the adjustment.

What we watch so you do not have to

Someone has to read the annual rule, the code set, and each plan’s bulletins. In a busy cardiology office, that rarely gets done.

We read them, and we turn each change into a check that runs before your claims go out. A deleted code does not reach a payer.
We also read every remittance against your contracts. If a payment comes in short, we raise it rather than absorbing it.
In-house vs. outsourced

How much can one biller cover in a cardiology practice?

An in-house biller knows your cardiologists and your patients. A cardiology practice also asks that person to bill visits, tests, procedures, the cath lab, and rehab, and to chase approvals for all of it. Outsourcing cardiology billing services brings people who handle each of those across many practices. Whether one desk can hold all of it is the honest question.
The questionOne in-house billerTruCare
ApprovalsChased the day of the appointmentFiled early and tracked to a decision
Diagnosis linkingChecked when a claim deniesChecked on every order before billing
Technical componentOften missed entirelyBilled wherever you own the equipment
Repeat studiesBilled plainly, then deniedChecked for the modifier and the reason
Cath lab and ASC claimsA second job nobody formally ownsSent alongside the physician’s claim
Cardiac rehabTracked by hand, if at allSessions counted against the program limits
Code changesNoticed when claims bounceBuilt into claim checks before they apply
Cost shapeSalary, benefits, training, softwareA percentage of collections, so it moves with volume
Absence and turnoverOne departure stalls billing for weeksStaffing the desk is on us
What the owner seesA report built on requestRevenue by physician and by service line, live
Compare against your numbersWant to see where your practice stands? Send us 90 days of denials and aging A/R.
Hover a state to see coverage
Where we serve

Cardiology billing in every state

We work with solo cardiologists, multi-site groups, electrophysiology and interventional practices, practices with their own imaging and cath labs, and groups choosing a cardiology billing company for the first time. Coverage rules differ by state and by plan, so we handle them one at a time rather than from a template.
Prior authorization
Technical and professional billing
Cath lab and ASC claims
Cardiac rehab
Multi-state enrollment
A named account contact
Who we bill every day
Medicare Part B
Coverage rules for tests and procedures, and the 2026 payment changes
Medicare Advantage
Authorization rules that differ plan by plan
Medicaid and managed Medicaid
State programs and MCO plans
BCBS and Anthem
Imaging and procedure policies that vary by plan
Centene family
Molina, WellCare, Amerigroup
Other
VA Community Care and self-pay
We bill whatever plans your practice is contracted with. If you are not contracted yet, TruCred handles the enrollment.

Cardiology billing saver guide

A practice collecting $1.25 million saves up to $41,935 a year by outsourcing to TruCare
In-house billingWith TruCareAnnual saving
Dedicated billing staff$73,060$0$73,060
Billing software and clearinghouseVariesIncluded—
Training, turnover, and coverageVariesIncluded—
TruCare fee (from 2.49% of collections)—$31,125—
Total annual cost$73,060$31,125$41,935
Example: a practice collecting $1.25 million a year with one full-time biller, at TruCare’s starting rate of 2.49%. Biller cost uses the BLS May 2025 median wage for medical records specialists ($51,140), with benefits at 30% of total compensation. Software and training costs vary by practice and are not counted. We do not replace your front desk, we take the claims work off it. Larger groups are quoted on volume rather than at the starting rate, so a bigger practice should not scale this example up.
Want this run on your own numbers?
Talk to a cardiology billing expert

After the first quarter

“We assumed our billing was fine because the visits were getting paid. What we could not see was the technical side of our studies, the approvals we were finding out about too late, and the repeat tests quietly denying. Once someone owned all of that, our revenue report looked like a different practice.”

Dr. Vikram Sethi
Managing partner, regional cardiology group

We use cookies to understand how visitors use our site and to improve your experience. You can accept or decline analytics cookies. See our Privacy Policy for details.